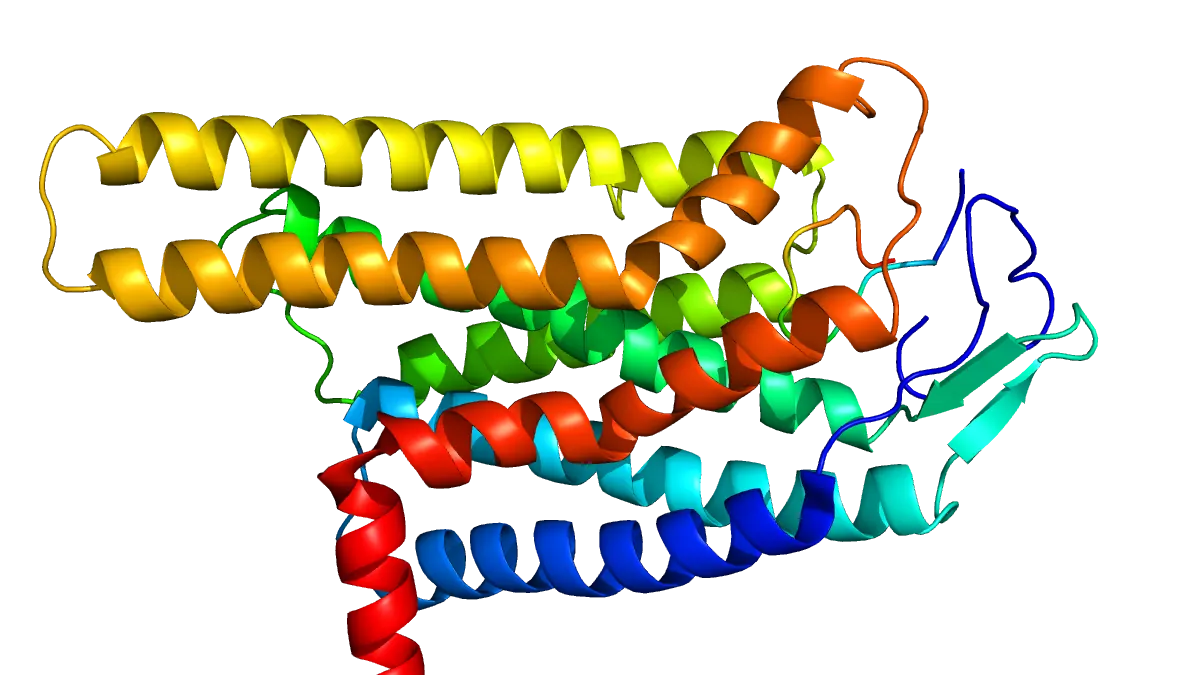
PT-141 is the development name for bremelanotide, a synthetic cyclic heptapeptide that activates several melanocortin receptors, with MC1R and MC4R the most relevant.
As Vyleesi, bremelanotide injection was approved by the US FDA on 21 June 2019 only for acquired, generalised HSDD in premenopausal women; it is not indicated for men or postmenopausal women.
Two phase 3 trials in 1,267 women reported statistically significant changes on desire and distress questionnaires, with nausea in 40% of treated patients.
Research-grade PT-141 is not Vyleesi: an approval covers a specific finished product and label, and the FDA decision does not make bremelanotide an approved medicine in Australia.
PT-141 is the development name for bremelanotide, a synthetic cyclic heptapeptide that activates melanocortin receptors. As Vyleesi, bremelanotide injection was approved by the US Food and Drug Administration on 21 June 2019 for one narrow indication: acquired, generalised hypoactive sexual desire disorder (HSDD) in premenopausal women. The label states it is not indicated for postmenopausal women or for men, and research-grade PT-141 is not Vyleesi.1,2,3
This overview explains what the molecule is, how it relates to melanotan II, what its receptor pharmacology involves, what the clinical trials reported, and exactly what the FDA did and did not approve.
What is PT-141?
PT-141 was developed by Palatin Technologies, whose scientists described it in 2003 as a synthetic peptide analogue of α-melanocyte-stimulating hormone (α-MSH) and an agonist at melanocortin receptors, including MC3R and MC4R, which are expressed mainly in the central nervous system.1 Its nonproprietary name is bremelanotide.4
The Vyleesi prescribing information describes bremelanotide acetate as "a synthetic, cyclic heptapeptide with a free acid at the carboxyl terminus and an acetylated amino group at the amino terminus", with the structure Ac-Nle-cyclo-(Asp-His-D-Phe-Arg-Trp-Lys-OH).3 The ring is a lactam bridge linking the side chain of aspartic acid at position 2 to that of lysine at position 7, and the peptide contains two non-standard residues: norleucine (Nle) at the N-terminus and D-phenylalanine in the middle of the ring.4
Ac-Nle-c[DHfRWK]-OH (norleucine has no standard one-letter code; lower-case f denotes D-phenylalanine)
Molecular formula
C50H68N14O10 (free base, PubChem and FDA label)
Molar mass
1025.2 g/mol (free base)
CAS number
189691-06-3 (free base); 1607799-13-2 (acetate)
PubChem CID
9941379
Other names
Bremelanotide, PT 141; Vyleesi is the US brand of bremelanotide injection
Origin
Synthetic analogue of α-MSH developed by Palatin Technologies
Formula, mass and CAS numbers are from PubChem; the formula and free-base molecular weight match the FDA label.3,4
How PT-141 relates to melanotan II
PT-141 and melanotan II share the same cyclic seven-residue sequence. PubChem's records show that the difference is at the C-terminus: melanotan II ends in an amide (C50H69N15O9, 1024.2 g/mol), while bremelanotide ends in a free carboxylic acid (C50H68N14O10, 1025.2 g/mol).4,5 Melanotan II was studied by researchers at the University of Arizona. In a 1998 double-blind crossover study of 10 men with psychogenic erectile dysfunction, eight developed erections after melanotan II, and nausea, stretching and yawning were reported more often than with placebo.6
The close structure does not mean a shared safety record. The FDA's page on bulk drug substances that may present significant safety risks in compounding cites published case reports of serious adverse events with melanotan II, including melanoma, posterior reversible encephalopathy syndrome, sympathomimetic toxidrome and priapism.7
How does bremelanotide work?
According to the prescribing information, bremelanotide "nonselectively activates several receptor subtypes", in the order of potency MC1R, MC4R, MC3R, MC5R, MC2R, and at therapeutic dose levels binding to MC1R and MC4R is most relevant. Neurons expressing MC4R are found in many areas of the central nervous system, while MC1R on melanocytes drives melanin production, which is the basis of the label's pigmentation warning. The label is explicit that "the mechanism by which VYLEESI improves HSDD in women is unknown".3
Animal work points to a central site of action. In rats, systemic PT-141 increased c-Fos immunoreactivity, a marker of neuronal activation, in the hypothalamus.1 In a 2004 study in female rats, PT-141 selectively increased solicitational, or appetitive, sexual behaviours without affecting lordosis, pacing, general motor activity or measures of sexual reward.8 The authors concluded that central melanocortin systems are important in regulating sexual desire in the female rat, and proposed the compound for study in female sexual desire disorders.8
The label also summarises the human pharmacokinetics of the approved product. After a single subcutaneous injection, the mean terminal half-life of bremelanotide was about 2.7 hours (range 1.9 to 4.0 hours), and its main metabolic pathway is hydrolysis of the amide bonds of the cyclic peptide.3 Those figures describe Vyleesi in clinical studies; they are not a property of any research-grade powder.
Palatin's early clinical studies of PT-141 were in men. Phase I studies of intranasal PT-141 in healthy men and in men with mild-to-moderate erectile dysfunction reported statistically significant erectile responses versus placebo, measured by RigiScan, with flushing and nausea the most common adverse events.9 A subcutaneous study in healthy men and in men with an inadequate response to sildenafil also reported significant erectile responses.10 The approved medicine that eventually emerged from the program is not indicated for men.3
Phase 2 and phase 3 trials in premenopausal women
Development then moved to female sexual dysfunction. Responder analyses from a phase 2b dose-ranging study in premenopausal women with HSDD, female sexual arousal disorder or both reported statistically significant responder rates versus placebo on all seven endpoints analysed, at the dose later taken into phase 3.11
The pivotal program, RECONNECT, comprised two identical 24-week, randomised, double-blind, placebo-controlled phase 3 trials (studies 301 and 302) that randomised 1,267 premenopausal women with HSDD.12 The co-primary endpoints were two questionnaire scores: the desire domain of the Female Sexual Function Index and item 13 of the Female Sexual Distress Scale–Desire/Arousal/Orgasm, which asks how often the participant felt bothered by low sexual desire.3,12 Participants had a mean age of 39, and 85.6% were white; the published report notes that most were enrolled at US sites, which is worth bearing in mind when generalising the results.12
Measure (RECONNECT)
What it assessed
Reported result, bremelanotide vs placebo
FSFI desire domain (co-primary)
Frequency and level of desire; score range 1.2 to 6.0
Efficacy figures are from the published trial report; the secondary endpoint and adverse-reaction rates are from the FDA label.3,12
To put the co-primary results in context: the FSFI desire score is calculated from two questions and runs from 1.2 to 6.0, and the label reports mean baseline scores of 2.0 to 2.1 in both trials. Mean changes from baseline were 0.5 to 0.6 points with bremelanotide and 0.2 points with placebo, so part of the improvement seen on the drug was also seen on placebo.3 That pattern is common in trials that rely on self-reported outcomes, and it is why the between-group difference, not the raw change, is the figure that matters.
Long-term data and an independent re-analysis
In a 52-week open-label extension, 684 of 856 eligible women enrolled and 272 completed it; the most common treatment-related adverse events were nausea (40.4%), flushing (20.6%) and headache (12.0%), and the authors reported no new safety signals.13 An independent 2021 re-analysis based on data in the FDA application found results similar to the published ones, but argued that the improvements were modest, that discontinuation because of adverse events was substantially higher with bremelanotide (odds ratio about 12), and that many outcomes pre-specified in the study plans went unreported.14 Both readings are worth knowing when citing the trials.
Vyleesi: what the FDA approved, and what it did not
The FDA approved Vyleesi (bremelanotide injection, NDA 210557) on 21 June 2019.2 The original prescribing information limits the indication to premenopausal women with acquired, generalised HSDD, defined as low sexual desire that causes marked distress or interpersonal difficulty and is not due to a co-existing medical or psychiatric condition, problems with the relationship, or the effects of a medication or drug substance.3
Limitations of use. Not indicated for HSDD in postmenopausal women or in men, and not indicated to enhance sexual performance.
Contraindications. Uncontrolled hypertension or known cardiovascular disease.
Warnings. A transient increase in blood pressure and decrease in heart rate after each dose; focal hyperpigmentation, reported by 1% of patients and including the face, gums and breasts; and nausea, reported by 40% of patients, with 13% needing anti-nausea medication and 8% stopping treatment.
An FDA approval attaches to a specific finished product made by a specific applicant, not to a molecule in general. Vyleesi is a sterile solution in a pre-filled, single-dose autoinjector with defined excipients, supplied under an approved application with its own labelling and post-marketing commitments.2,3 A lyophilised PT-141 powder sold for laboratory research is none of those things and carries none of that approval. The approval is also a US decision: it does not by itself make bremelanotide an approved medicine in Australia. For how Australian law treats research compounds, see are research peptides legal in Australia? PT-141 is supplied for laboratory research only.
Reading PT-141 research in the laboratory
Four points are worth keeping in mind when using the bremelanotide literature:
The clinical evidence is specific. It concerns subcutaneous bremelanotide in premenopausal women with a defined diagnosis, measured on questionnaire endpoints. It does not extend to other populations, and the label says so.3
The pharmacology spans several receptors. Activity at MC1R and MC4R, among others, means that pigmentation, blood-pressure and nausea findings are part of the compound's profile rather than incidental observations.3
The endpoints are self-reported. Questionnaire scores improved on placebo as well as on the drug, so between-group differences and responder analyses are the relevant numbers, and an independent re-analysis has questioned how complete the reporting was.3,14
Identity needs care. Bremelanotide and melanotan II differ by about 1 g/mol, the difference between a free acid and an amide at the C-terminus, which is small enough to be missed by low-resolution mass measurements. Confirming the free-acid form calls for high-resolution mass spectrometry or chromatography against a reference standard.4,5
Yes. PT-141 was the development name used by Palatin Technologies, and bremelanotide is the nonproprietary name of the same cyclic heptapeptide. Vyleesi is the US brand of the approved bremelanotide injection. A research-grade PT-141 powder has the same intended structure but is not Vyleesi and carries none of that product approval.
Is PT-141 FDA approved?
Bremelanotide was approved by the US FDA on 21 June 2019 as Vyleesi, an injection for premenopausal women with acquired, generalised hypoactive sexual desire disorder. The label says it is not indicated for men, for postmenopausal women or to enhance sexual performance. The approval covers that specific product, not research-grade PT-141.
How does PT-141 work?
Bremelanotide activates several melanocortin receptors, with MC1R and MC4R described as most relevant at therapeutic levels. MC4R is found on neurons in many brain regions, and MC1R on pigment cells. Rat studies point to a central action, but the FDA label states that its mechanism in hypoactive sexual desire disorder is unknown.
What is the difference between PT-141 and melanotan II?
They share the same cyclic seven-residue sequence. Melanotan II ends in a C-terminal amide, while bremelanotide ends in a free carboxylic acid, a difference of about 1 g/mol. They are separate compounds with separate records: bremelanotide went through phase 3 trials and FDA approval, while the FDA cites serious adverse-event reports for melanotan II.
What side effects were reported in bremelanotide trials?
In the phase 3 trials summarised on the FDA label, nausea affected 40.0% of women on bremelanotide versus 1.3% on placebo, flushing 20.3% versus 0.3%, and headache 11.3% versus 1.9%. The label also warns of transient blood-pressure rises after each dose and focal hyperpigmentation in 1% of patients.
References
Molinoff PB, Shadiack AM, Earle D, Diamond LE, Quon CY. PT-141: a melanocortin agonist for the treatment of sexual dysfunction. Ann N Y Acad Sci. 2003;994:96-102. PubMed 12851303
US Food and Drug Administration. NDA 210557 approval letter, Vyleesi (bremelanotide) subcutaneous injection, 21 June 2019. Source
US Food and Drug Administration. VYLEESI (bremelanotide injection), for subcutaneous use. Prescribing information, NDA 210557, revised June 2019. Source
National Center for Biotechnology Information. PubChem Compound Summary for CID 9941379, Bremelanotide. Accessed September 2026. Source
National Center for Biotechnology Information. PubChem Compound Summary for CID 92432, Melanotan-II. Accessed September 2026. Source
Wessells H, Fuciarelli K, Hansen J, et al. Synthetic melanotropic peptide initiates erections in men with psychogenic erectile dysfunction: double-blind, placebo controlled crossover study. J Urol. 1998;160(2):389-93. PubMed 9679884
US Food and Drug Administration. Certain Bulk Drug Substances for Use in Compounding that May Present Significant Safety Risks (content current as of 22 April 2026). Source
Pfaus JG, Shadiack A, Van Soest T, Tse M, Molinoff P. Selective facilitation of sexual solicitation in the female rat by a melanocortin receptor agonist. Proc Natl Acad Sci U S A. 2004;101(27):10201-4. PubMed 15226502
Diamond LE, Earle DC, Rosen RC, Willett MS, Molinoff PB. Double-blind, placebo-controlled evaluation of the safety, pharmacokinetic properties and pharmacodynamic effects of intranasal PT-141, a melanocortin receptor agonist, in healthy males and patients with mild-to-moderate erectile dysfunction. Int J Impot Res. 2004;16(1):51-9. PubMed 14963471
Rosen RC, Diamond LE, Earle DC, Shadiack AM, Molinoff PB. Evaluation of the safety, pharmacokinetics and pharmacodynamic effects of subcutaneously administered PT-141, a melanocortin receptor agonist, in healthy male subjects and in patients with an inadequate response to Viagra. Int J Impot Res. 2004;16(2):135-42. PubMed 14999221
Althof S, Derogatis LR, Greenberg S, et al. Responder Analyses from a Phase 2b Dose-Ranging Study of Bremelanotide. J Sex Med. 2019;16(8):1226-1235. PubMed 31277966
Kingsberg SA, Clayton AH, Portman D, et al. Bremelanotide for the Treatment of Hypoactive Sexual Desire Disorder: Two Randomized Phase 3 Trials. Obstet Gynecol. 2019;134(5):899-908. PubMed 31599840
Simon JA, Kingsberg SA, Portman D, et al. Long-Term Safety and Efficacy of Bremelanotide for Hypoactive Sexual Desire Disorder. Obstet Gynecol. 2019;134(5):909-917. PubMed 31599847
Spielmans GI. Re-Analyzing Phase III Bremelanotide Trials for "Hypoactive Sexual Desire Disorder" in Women. J Sex Res. 2021;58(9):1085-1105. PubMed 33678061
Research use only. This article summarises published scientific literature
for educational purposes. It is not medical advice and does not describe or endorse human
or veterinary use. Compounds supplied by Titan Peptides are for laboratory research only
and are not approved therapeutic goods in Australia.
What the TGA, the June 2026 Poisons Standard, the Therapeutic Goods Act and customs law actually say about peptides, "research use only" labels, importing and advertising in Australia.
A plain-English primer on research peptides: what a peptide is, how peptides are built one amino acid at a time on a resin bead, why they arrive as a freeze-dried powder, and what "research use only" does and does not mean.
A section-by-section guide to reading a peptide certificate of analysis: identity, HPLC purity, net peptide content, counter-ions, water, endotoxin, and the red flags that mean a COA does not check out.